Pulmonology

Addressing the increase in pediatric sleep disorders

The Children’s of Alabama Sleep Disorders Center is taking a multifaceted approach to pediatric sleep disorders. (Stock photo)

Pediatric sleep disorders affect 25-40% of children and adolescents in the U.S. However, the incidence is increasing, said Brad Troxler, M.D., who directs the Children’s of Alabama Sleep Disorders Center. The reasons for the increase are multi-factorial, Troxler said, but the problems are exacerbated by expanding screen time, which affects the quality of sleep; childhood obesity, which increases the risk of obstructive sleep apnea and other sleep disorders; and the after-effects of the pandemic, when sleep schedules were disrupted. Troxler and his team are addressing the increase through innovation, research and training.

About the center

The Children’s Sleep Disorders Center is the only multidisciplinary pediatric sleep disorders program in Alabama and one of just a handful of in the country. It features a 12-bed unit, in which the team performs about 2,000 overnight sleep studies and up to 100 daytime studies each year. Most patients are seen for insomnia, daytime sleepiness and snoring, as well as chronic conditions like sleep apnea, narcolepsy, idiopathic hypersomnia and periodic limb movement disorders.

Troxler

The pediatric sleep program differs significantly from adult programs in its approach, Troxler said. “Certainly, a pediatric sleep program is going to be much more patient and family centered and more holistic than what you might see in an adult sleep center,” he added. In addition, it requires more technicians and nurses—usually one for every two patients—to make children, especially those with autism or other developmental disabilities, feel comfortable with the electrodes and other equipment required for a sleep study.

“Pediatric patients require lengthier visits,” sleep specialist Mohini Gunnett, M.D., said. “And there’s definitely a need for more specialized protocols for the complex scenarios children can present with.” The team also manages many comorbidities associated with sleep disorders, particularly pulmonary conditions.

Innovation

“We are always trying to create and improve on innovative models of care,” said Gunnett, who’s also an assistant professor in the Division of Pulmonary and Sleep Medicine. For instance, she recently worked with pediatric otolaryngologist Philip Rosen, M.D., to implant the first pediatric patient with an upper airway stimulation device to assist with management of sleep apnea.

Gunnett

This nerve stimulator device, which is currently approved for patients with Down syndrome, works by producing gentle pulses to the nerve that controls airway muscles and tongue movement, helping keep the airway open and the tongue protruded forward so breathing is more comfortable during sleep.

“We are excited to see how this intervention can help manage sleep apnea in a population that often struggles to achieve control of their sleep apnea with conventional positive airway pressure therapy alone,” Gunnett said.

Research

Research is also becoming more of a focus in the program. Anis Nourani, M.D., an assistant professor in the Division of Pediatric Pulmonary and Sleep Medicine, is creating a database that can be used for research and quality improvement projects, and the team recently received multiple grants to study behavioral modifications for certain sleep disorders. Several other grants are pending. “The research component is growing and adding to the fun of the job,” Gunnett said. “Hopefully, it will lead to even better patient care improvement and growth in our group.”

Training

Nourani also serves as the director of the Sleep Medicine Fellowship Program, which is one of the few programs of its kind in the country, training a pediatric and an adult specialist each year. Nourani says the fellowship is crucial given a significant shortage of pediatric sleep specialists nationwide. Currently, there are only about 420 pediatric board-certified sleep medicine specialists in the U.S., or just 0.51 sleep physicians for every 100,000 children.

Nourani

To address this gap, the team at Children’s is working to incorporate more sleep education into the curriculum for medical students and residents, hoping to spark interest in the field and encourage more trainees to pursue sleep medicine fellowships. Students are also now rotating through the center. And, as more research emerges about the complex relationship between sleep and health, more practitioners are becoming interested in the field, Nourani said, including those from primary care, pulmonary medicine, neurology and anesthesiology.

The basics

Despite new technology and innovative treatments for sleep disorders, the basics for getting a good night’s sleep remain the same: “Creating a consistent bedtime routine that limits screen time and does not vary widely from day to day,” Troxler said.
Neurology & Neurosurgery

Procedure and device offer new options for epilepsy patients

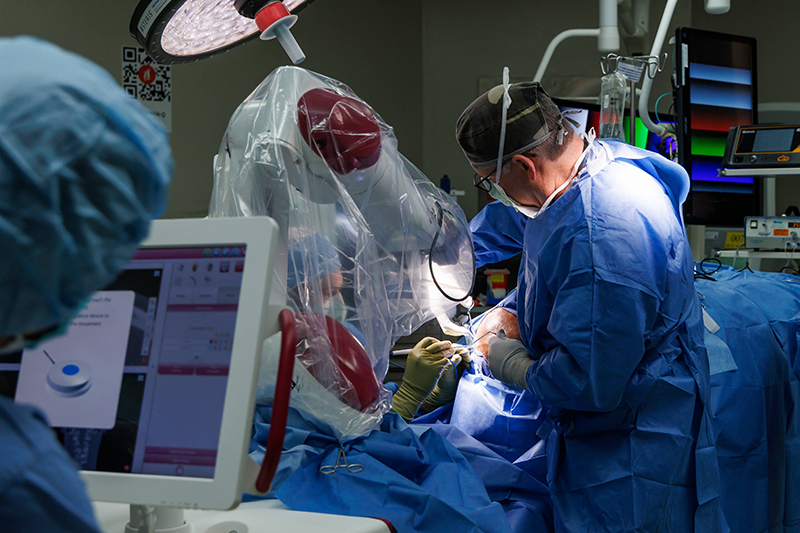
Curtis Rozzelle, M.D., performing a deep brain stimulation procedure for epilepsy.

In January 2024, a University of Alabama at Birmingham (UAB) pediatric neurosurgeon performed the first deep brain stimulation (DBS) procedure for epilepsy at Children’s of Alabama, offering a new treatment option for pediatric patients who experience drug-resistant seizures.

During the procedure, Curtis J. Rozzelle, M.D., a professor in the UAB Department of Neurosurgery, also implanted the first NeuroPace responsive neurostimulation (RNS) epilepsy treatment device at Children’s.

The NeuroPace RNS ® System, which consists of a small generator attached by leads to electrodes, was designed to communicate with a computer to record brain activity, recognize seizure-related patterns and deliver stimulation to suppress seizures. The device, which is curved for better placement within the skull, monitors brainwaves constantly and can be customized on a patient-by-patient basis.

“Much like a cardiac pacemaker that senses and responds to abnormal heart rhythms, this combination of technologies will detect brain activity that precedes seizures, then stimulate pathways deep in the brain to either prevent seizures from starting or stop seizure activity in its tracks,” Rozzelle said.

When performing a DBS procedure, a neurosurgeon inserts electrodes connected to a neurostimulator into the brain to disrupt epileptic electrical activity before it can cause a seizure. Similar to the RNS System, the DBS neuromodulation device can be programmed after placement in an outpatient clinic by an epilepsy specialist, like UAB Department of Pediatrics Division of Neurology professor Monisha Goyal, M.D.

In this case, Rozzelle placed the RNS® System electrodes in the thalamus, resulting in a twofold RNS and DBS procedure. 

Neurostimulators have long been used to treat various neurological disorders when traditional treatment options fail. DBS was originally developed in 1997 to treat Parkinson’s disease and has since expanded as a treatment option for epilepsy, dystonia and more. RNS gained initial FDA approval in 2013 and has proved to be effective in many patients. Presently, RNS is FDA-approved only for adults, but is successfully being used off label in the pediatric population.

Though DBS and RNS are not viable options for all patients, they show tremendous potential in treating children with epilepsy who need more innovative treatment options. “With this first RNS implantation [at Children’s of Alabama], we have expanded the armamentarium of therapies available to individuals with poorly controlled epilepsy,” Goyal said. “Unfortunately, neuromodulation with RNS is only [FDA-approved] for individuals who are at least 18 years old. The pediatric epilepsy team at Children’s of Alabama hopes that this therapy will be available to more children of Alabama soon.”

Cardiology

Saving lives in Latin America

Each year, a team from Children’s of Alabama travels to Peru to provide cardiovascular surgeries through Heart Care International.

For Children’s of Alabama cardiac pediatric intensivist Santiago Borasino, M.D., traveling to Peru each year as part of a team providing cardiovascular surgeries to children offers him a special way to give back to his home country.

The trips are sponsored by Heart Care International, a nonprofit organization committed to saving the lives of children born with congenital heart defects. Volunteer medical teams come from cardiac centers throughout the United States, including Children’s of Alabama, to provide care throughout Latin America.

Borasino’s first trips were to Chiapas, Mexico, but since he learned about the organization’s work in Peru, he has focused his efforts there.

Santiago Borasino, M.D.

“I get to give back to my country,” he said. “There’s always a lot of guilt for leaving. And so I get to go there, help with surgeries and give back to the country some—a little bit. This teeny tiny bit probably doesn’t repay everything that the country has done for me, but it’s a little bit. It’s very special to me.”

The team—which most recently included Children’s cardiothoracic surgeon Robert Sorabella, M.D.; pediatric cardiac anesthesiologists Jack Crawford, M.D., Ph.D., and Patrick Hussey, M.D.;  and Stephanie McBride, RNFA—works with doctors at the Instituto Nacional de Salud del Niño (INSN) San Borja in Lima, where Borasino was raised and attended medical school.

The local doctors coordinate with the visiting clinicians to choose the cases. “We can’t do cases that are too complex because we don’t have ECMO,” Borasino said. ECMO, or extracorporeal membrane oxygenation, is a life-support machine that can temporarily replace the heart and lungs. They also want the child to be able to recover before the team leaves, so they have to choose wisely, he added.

The visiting team works closely with their Peruvian counterparts. The American and Peruvian surgeons, anesthesiologists and nurses team up for surgeries, while Borasino partners with his Peruvian counterpart to manage the post-operative care side in the ICU. They generally perform about 15 surgeries a day.

Over his six trips to Peru, Borasino has witnessed significant growth in the skills and knowledge of the local medical professionals, most of whom were just starting to practice when he met them. “They’ve grown just like any doctor in the United States grows from being a young doctor who hasn’t done this too much to somebody who’s done it quite a lot.”

“The ultimate goal is that they will be independent,” he said. “They’re never going to be like Americans because of the resources. But, in theory, they could get close, at least for the moderate or low cases, a little complex but not too complex.”

Without these volunteer trips, the outlook for many of the young heart patients is grim. “Some of them will be lucky enough to get surgery within the system,” Borasino said. “And some of them will die. Not immediately, but eventually. Like in a few years without surgery, you end up dying. All these congenital heart diseases eventually kill you, either in weeks, months or years.”

However, the team’s work can be life-changing for the patients they’re able to help.

“The families are so thankful,” Borasino added. “Some come back every year when they know we’re there just to say hi, to bring their kids and tell us, ‘You saved our kid’s life.'” “It’s an opportunity to see more than just cardiac medicine,” he added. “And just to help.”

Hematology and Oncology

Leading with a focus on the patient

Katie Metrock, M.D., manages one of the nation’s largest pediatric neuro-oncology programs at Children’s of Alabama.

According to data from the CDC, brain and spinal tumors are the leading cause of death among childhood cancer patients. Katie Metrock, M.D., director of the pediatric neuro-oncology program at Children’s of Alabama, says being diagnosed with one of these cancers is “one of the scariest things that can happen to a family.”

The program, which is part of the Alabama Center for Childhood Cancers and Blood Disorders at Children’s, is one of the largest in the U.S. It offers a focus on treating children and adolescents with brain and spinal cord tumors as well as neurofibromatosis, a genetic condition that predisposes children to tumors. It is a leading center for clinical studies and basic research into these conditions, and it offers a neuro-oncology fellowship. Metrock took over as director of the program in October 2023.

“It is my goal that every patient that comes through this door feels like they have a team of people that are fighting for them,” she said. “I don’t want any patient to ever feel like they’re alone or any family to feel like they needed more.”

For Metrock, the battle has a personal element to it. When she was young, her aunt developed a brain tumor, and Metrock remembers visiting her in the hospital. “I was very fascinated by all that was happening,” she said. Her aunt “did quite well,” she added, and the experience sparked her interest in the treatment of brain tumors. In college, that interest grew when she worked at a camp for children with cancer and met a young patient with a brain tumor.

“So when I went to medical school and residency, I tried to keep an open mind and looked at all the different types of fields,” Metrock said. “But I think ultimately I knew this is the space I wanted to be in—to help these children and to improve their treatment options.”

Now, that’s her daily goal. As the program’s director, she leads a team that includes four pediatric neuro-oncologists, three pediatric nurse practitioners, child life specialists, chaplains, social workers, neuropsychologists and researchers. They collaborate closely with neurosurgeons, neurologists, advanced/palliative care physicians and radiation oncologists to provide comprehensive care tailored to each patient’s needs.

“It takes all of us working together to help patients and their families through this entire process,” Metrock said. “Ever since coming here to Children’s, I have been blown away with the teamwork approach.”

The center’s mission extends to research, which is desperately needed, Metrock added. “We have to do better for these kids,” she said. “Making research at the forefront of our mission is huge.”

To that end, the program participates in several clinical trial research consortia, including the Children’s Oncology Group, the Pediatric Neuro-Oncology Consortium (PNOC), and the Sunshine Project. The partnerships allow Children’s to offer leading-edge clinical trials to patients while contributing to the broader advancement of the field.

For instance, researchers are investigating methods to deliver medications more effectively across the blood-brain barrier, which remains one of the greatest challenges to improving survival. They also are conducting clinical trials into less invasive, safer and more effective treatments for tumors like medulloblastoma, craniopharyngioma and germ-cell tumors. Additionally, they’re exploring vaccines to target high-grade gliomas.

The program is also expanding its educational reach globally. A new partnership with St. Jude Children’s Research Hospital aims to develop educational programs in neurofibromatosis for areas with limited expertise in treating neurofibromatosis-related tumors. The team also has a partnership with Washington University School of Medicine in St. Louis for a global neuro-oncology fellowship.

The primary focus, however, remains the child. “When a child comes in, the first thing we need to know is what type of tumor do they have and how do we treat it,” Metrock said. “But I think you can get tunnel vision with that. You really have to see that this is a child, and they have their whole life around them and then the life that they’re going to move forward with after this. So how do we meet them where they’re at and how do we help them move forward with the best success possible?” Those are the questions she aims to answer for each patient.

Nephrology

Improving care for children with TSC

The Children’s nephrology team is working with the UAB Tuberous Sclerosis Clinic to improve the care of children with TSC.

Tuberous sclerosis complex (TSC) is a rare genetic condition in which non-cancerous tumors grow in various body organs. It affects about one in 1 million births. Although primarily viewed as a neurological condition, it requires multidisciplinary care since the tumors may appear in any organ, particularly the kidneys. That’s why Children’s of Alabama’s nephrology specialists have become more involved with the University of Alabama at Birmingham’s Tuberous Sclerosis Clinic, one of only 10 in the country designated as a Center of Excellence by the TSC Alliance.

Between 50% and 75% of patients with TSC develop benign tumors in their kidneys, called angiomyolipomas, pediatric nephrologist Daniel Feig, M.D., Ph.D., said. They rarely cause symptoms, but can crowd out kidney function, squashing blood vessels adjacent to the tumors, resulting in high blood pressure. If they get much bigger than 3 to 4 cm, he said, “there’s a very, very high risk of them bleeding.” Such bleeding could be life threatening. Medications called mTOR inhibitors can shrink the tumors and may prevent their recurrence after surgery.

About 5% of patients with TSC develop a more serious cystic kidney disease called polycystic kidney disease, the result of yet another genetic mutation. “They can progress to kidney failure because the cysts replace the normal functional tissue in the kidneys.” There isn’t much available to treat the condition, Feig said, other than monitoring and managing blood pressure. About 3% of people with TSC will develop kidney cancer.

The weekly tuberous sclerosis clinic is directed by Martina Bebin, M.D., a pediatric neurologist at Children’s; and Bruce Korf, M.D., Ph.D., a pediatric neurologist who also specializes in genetics. “Over the last year we’ve worked to improve the communication between the pediatric neurology and nephrology groups as well as becoming more involved with the Tuberous Sclerosis Alliance,” Feig said. “That includes presentations for families about the optimal care of pediatric patients and how to avoid complications.”

Feig and his team are also involved in clinical trials to manage renal tumors and identify agents that can shrink them, thus avoiding surgery or even kidney loss. Screening is key, he said, “so we can identify when children need interventions.” In addition, understanding the growth parameters of the tumors and how they link to the two genetic mutations that cause the disease enables clinicians to personalize care and “take some of the guesswork out of how we’re monitoring these patients.”

People with TSC may be diagnosed in utero if an ultrasound shows the presence of tumors in the heart, called rhabdomyomas. Some are diagnosed after birth because of hypopigmented macules on the skin that look like the leaves from an ash tree. Seizures during the first year of birth are another clue, but many children aren’t diagnosed until they demonstrate developmental delays when they start school.

With only two Centers of Excellence in the Southeast, Feig said, “We’re situated to help provide care for our region and extending far beyond Alabama.”

Nephrology

Testing the first potential treatment for AMKD

Daniel Feig, M.D., Ph.D., and other Children’s researchers are leading a trial that provides hope for patients with AMKD.

A team of clinicians and researchers from Children’s of Alabama and the University of Alabama at Birmingham (UAB) has launched a potentially groundbreaking clinical trial testing the first potential treatment for APOL1-mediated kidney disease, or AMKD, a genetic condition linked to mutations in the APOL1 gene that can lead to rapid kidney function decline and, ultimately, kidney failure.

“The gene itself is involved in activation of inflammatory arms of the immune system,” said Daniel Feig, M.D., Ph.D., a pediatric nephrologist at Children’s. The APOL1 gene variant doesn’t just cause AMKD; it also exacerbates other kidney conditions. “Individuals with focal segmental glomerulosclerosis (scarring in the kidneys), IgA nephropathy, or diabetic nephropathy with APOL1 risk variants progress to end-stage kidney disease much faster than those without the risk variants.”

This genetic factor is particularly common in African Americans, contributing significantly to the higher rates of kidney failure seen in this population, Feig said.

The current trial, called AMPLITUDE, is testing the efficacy and safety of a first-in-its-class oral medication called VX-147, or inaxaplin. The drug is designed to inhibit the inflammatory pathway triggered by the APOL1 gene variant. The hope is that blocking this pathway will slow or even stop the progression of AMKD.

“It’s exciting because these patients have no other options for therapy,” Feig said.

An earlier trial evaluating standard-of-care plus inaxaplin in people with two APOL1 variants showed a nearly 50% reduction in proteinuria (a marker of kidney damage) after 13 weeks of treatment and reduction in scar tissue in the kidneys. The most common side effects were headache, back pain and nausea. The study was published in the New England Journal of Medicine.

The current trial is enrolling about 500 adult and pediatric participants, including about 150 children ages 10 to 18. More than 200 centers in the U.S. and other countries are involved.

Those eligible for the trial must have confirmed AMKD (with two APOL1 variants), proteinuria, and reduced kidney function. Participants will be monitored for two years while taking the study medication.

“If we can slow the disease by a number of years, that means these patients don’t need dialysis, they don’t need transplant, they don’t have the risk of kidney failure and their life expectancy is much, much, much longer,” Feig said. “It offers hope to families that have been having a difficult time and are really frustrated by the lack of alternatives.”

Neonatology

Innovative Lung Testing for Preemies

A device developed by Children’s of Alabama neonatologists is showing promise at measuring lung function in premature babies.

One of the most important parameters of a premature baby’s health status is respiratory health. How well are their lungs working? What long-term respiratory complications might occur from the premature birth? Yet assessing lung function in these fragile newborns has long been a complex and invasive process.

“Right now, we diagnose lung disease based on whether a baby needs oxygen or not,” Children’s of Alabama neonatologist Colm P. Travers, M.D., said. “But we don’t know how severe their lung disease is and what type of lung disease they have.”

Measuring lung function in children and adults is as simple as having them blow hard into a plastic tube. Pulmonary function testing in neonates, however, requires complicated equipment as well as sedation or anesthesia, limiting its use outside of research studies.

Colm Travers, M.D.

So, Travers and his team have brought a decades-old technology used in adults called forced oscillation technique (FOT) to the NICUs at the University of Alabama at Birmingham (UAB) and Children’s. They worked with the device manufacturer to develop a machine designed for small babies. It sends sound waves into the lungs while the infant is sleeping and breathing naturally. The sound waves then bounce off the lungs, providing information on stiffness and resistance in the airways. It can be performed in less than 30 seconds, non-invasively, without sedation and repeated over time. It typically takes just a few minutes to set up and can be used soon after birth.

“It’s well suited to neonates because it doesn’t need any effort on behalf of the baby,” Travers said. “Oscillometry is also able to tell you the severity and the type of lung disease a baby has.” In addition, he said, it’s an ideal tool to use in research because of its simplicity and accuracy.

The Children’s team has already used the device in more than 600 neonates. They published the first results of their work in 2020, which demonstrated the feasibility of using oscillometry in healthy newborns and those with respiratory disorders. Now, they’re in the midst of a larger study funded by the National Heart, Lung, and Blood Institute involving 550 babies with the goal of establishing normative data for infant lung function and tracking outcomes, such as asthma and wheezing, in early childhood.

“We’re also using it in our NICU to see whether babies respond to certain medications,” Travers said. This approach could help doctors quickly determine if a treatment is effective or if they need to pursue alternative options.

The use of FOT at Children’s is still only in the research phase. Travers says he and his team are still following the infants until they are 2 years old. “In the future, we hope to see the infants back around the time they are starting school so we can see how they are doing in terms of exercise capacity and lung function,” he said.

Eventually, Travers hopes FOT will become standard of care not only in his NICU, but in hospitals everywhere.

Neonatology

Risk factors for BPD-PH in preterm infants

Studies led by Children’s neonatologists show early indicators of bronchopulmonary dysplasia with pulmonary hypertension.

It’s well-known that preterm infants are prone to breathing difficulties due to their underdeveloped lungs. But the most common lung disease in these babies, bronchopulmonary dysplasia (BPD), is only recently becoming better understood more than a half-century after it was first described.

Now, Children’s of Alabama neonatologist Samuel Gentle, M.D. is expanding that knowledge by focusing on the most severe type of BPD—the form associated with pulmonary hypertension (PH)—in research that teases out contributing factors to this deadly disease.

It’s a major threat: nearly half of preterm infants develop BPD, which can lead to long-term breathing and health problems. About 20% of these babies also develop PH, and an estimated 40% of them will die of BPD-PH before turning 2 years old.

Samuel Gentle, M.D.

“This is a disease for which there’s growing research interest. It can be lethal, is not uncommon in extremely preterm infants, and we have little understanding of how to prevent or treat it,” said Gentle, who’s also an assistant professor of neonatology at the University of Alabama at Birmingham (UAB). “And children who do survive have long-term complications that persist into adulthood. It’s not a disease they just grow out of.”

“I’ve also had many interactions with families who lost a child to this,” he added. “Oftentimes, a child will be stable and doing well, and then collapse. I’ve seen how this can ravage a family.”

Since research has been scant about what causes the development of BPD-PH—as well as how to screen, treat and prevent it—Gentle wanted to fill the vacuum. Currently, a single ultrasound of the heart is the standard diagnostic method, though UAB performs this testing more frequently.

“We need to get better at identifying this disease in real time, rather than doing ultrasounds at arbitrary time intervals,” Gentle said. “Even with UAB’s testing approach, I believe it will become possible to diagnose it sooner, allowing earlier initiation of PH-targeted therapies.”

Along with UAB colleagues, Gentle published two studies that assessed factors that may contribute to BPD-PH in preterm babies. Published in the American Journal of Respiratory and Critical Care Medicine, they found two important associations: The duration of intermittent hypoxia events and the presence and persistence of a patent ductus arteriosus (PDA) after birth are both novel risk factors for BPD-PH.

In the first study, Gentle found that infants who experienced intermittent hypoxia events lasting longer than one minute were twice as likely to develop BPD-PH. “If an infant has longer intermittent hypoxia events, we might be more proactive in screening that infant for BPD-PH,” he said.

In the second study, preterm babies born with BPD-PH between 22 and 28 weeks’ gestation were more likely to have a PDA vessel that stayed open longer than 28 days. Babies with longer PDA duration were also more likely to die due to complications of BPD-PH than infants with only BPD. “The PDA could be interfering with the development of pulmonary vasculature resulting in PH,” Gentle said.

UAB will be participating a multicenter trial to determine whether closing PDAs with a catheter-closure device might lower the risk of this PH variant. But far more study is needed, Gentle pointed out.

“While this research focused on a specific phenotype of BPD, we need a comprehensive approach to identifying each infant’s specific type of lung disease from which we can decide on the best therapeutic course for every child,” he said.

Urology

A new model for testicular torsion detection

Residents practicing testicular torsion detection using a new model created by the Children’s Pediatric Simulation Center

Testicular torsion is a serious medical emergency that requires immediate surgical intervention. It occurs when the spermatic cord twists, cutting off blood flow to the testicle. If not treated promptly, the condition can lead to permanent damage or loss of the affected testicle.

“Time is testicle,” said Carmen Tong, D.O., a pediatric urologist at Children’s of Alabama. “Pretty much every minute counts when it comes to testicular torsion.” Indeed, the so-called “golden window” to salvage testicular function after symptom onset is between four and eight hours. Any longer not only affects long-term testicular function but increases the risk of orchiectomy, or the removal of one or both testicles. “That can be devastating,” Tong added.

So prompt diagnosis is crucial. Yet the condition may present with vague symptoms such as abdominal pain and nausea. To improve diagnosis, Tong turned to pediatric intensivist Nick Rockwell, M.D., and advanced nurse educator Autumn Layton, MSN, RN, in the hospital’s Pediatric Simulation Center. Together, they created a testicular torsion model that provides hands-on training for residents.

The initiative came about after a teenaged boy’s torsion was missed. That begged the question: “Is there a way we can work with our trainees to give them a better understanding of something that’s a rare event, but when it happens, is a high-stakes situation,” Rockwell said.

From left: Carmen Tong, D.O.; Nick Rockwell, M.D.; Autumn Layton, MSN, RN

Rockwell, Layton and their team used Play-Doh-covered Styrofoam balls to simulate a torsed testicle, while a stress ball represents a normal testicle. These are enclosed in balloons to mimic scrotal skin and attached to a mannequin. Residents can then practice palpating the model to distinguish between normal and torsed testicles, providing a “full, immersive experience,” Rockwell said.

The students are told the mannequin is a 15-year-old boy admitted the night before for abdominal pain that is getting worse. Rockwell “plays” the patient, responding to questions. He can also adjust the mannequin’s vital signs, such as increasing heart rate if the trainees do something painful during the exam.

Next up for the training is a series of mannequins: one is normal while three others depict the disease at different stages. This helps learners distinguish which testicle is torsed, or if the testicle is inflamed (epididymitis). Through this exercise, trainees learn the Testicular Workup for Ischemia and Suspected Torsion (TWIST) score, which identifies children at risk of testicular torsion. The higher the score, the more urgent the need for immediate treatment.

The response to the training been overwhelmingly positive, Tong said. In addition, “what’s super impressive about this model is that it’s easily replicable. So once we publish this, other institutions can take what we did and create the same model. It doesn’t cost thousands of dollars.”

Orthopedics

Orthopedics team expands to meet increased demand

From left: Anna Stephens, MSN, CRNP; Shane Strom, M.D.; and Mallory Myers, PA

As the only stand-alone children’s hospital in the state and the sole tertiary referral center, Children’s of Alabama already fielded a robust demand for orthopedic services. But steady population growth in the Birmingham area—combined with lengthening waits for clinic appointments—have prompted Children’s to expand its orthopedic team to accommodate the need.

Since late 2022, the team has added two orthopedic surgeons and two advanced practice providers. The division now has six surgeons and four advanced practice providers. These empower the department to meet patients’ needs as demand increases. That has continued at a clip of 10% to 20% year over year since 2020, says orthopedic surgeon Kevin Williams, M.D., who came to Children’s four years ago.

“We’re constantly looking to provide better care for children of Alabama,” said Williams, who’s also an assistant professor of orthopedic surgery at University of Alabama at Birmingham (UAB). “One way was to put more providers in place who can take care of these patients in clinic and think about how to best care for children with difficult pathologies.”

Several thousand young patients seek inpatient and outpatient orthopedic care at Children’s each year. The most common conditions the team treats include fractures around the elbow—which comprise up to 70% of orthopedic surgeries at Children’s—along with scoliosis, hip dysplasia, cerebral palsy and other spastic neuromuscular conditions.

“There’s just an overflow of patients, so provider schedules were extremely full, and they were booking appointments months and months out,” explained pediatric nurse practitioner Anna Stephens, MSN, CRNP, who joined the department in 2023 after working in several capacities at Children’s since 2017. “More providers were needed to get patients seen in an appropriate time frame.”

The new faculty and staff members not only round out the department roster, but also add flexibility to everyone’s roles, said orthopedic surgeon Shane Strom, M.D., who joined in September 2023 after completing a fellowship in at Scottish Rite for Children in Dallas.

Advanced practice providers can see patients independently, freeing up surgeons for surgical cases. They can also assist in the operating room, Williams notes, “which, with the increase in OR numbers, has been really helpful.”

But, “not everything we do is surgical,” said Strom, who’s also an assistant professor of pediatric orthopedics at UAB. “With clinic numbers being higher and wait times to get in to see a provider longer, adding advanced practice providers can help with non-operative care, such as casting or treating club feet with bracing.”

Physician assistant Mallory Myers, PA, who joined the department in February 2023, agrees. “The expansion allows surgeons to have more time focusing on complex patients and surgical patients without making non-surgical patients wait longer times to be seen,” she said. “Also, nurse practitioners and physician assistants have a similar clinical scope, but the way we’re trained is different, so it’s a benefit to have multiple points of view.”