Browsing Tag

pediatrics

Gastroenterology

Expanding to Improve Patient Care

To improve patient care, the Children’s Division of Gastroenterology, Hepatology and Nutrition has added six new faculty members.

When Sandeep Gupta, M.D., arrived at Children’s of Alabama and the University of Alabama at Birmingham (UAB) as chief of the Division of Pediatric Gastroenterology, Hepatology and Nutrition in 2023, he immediately recognized the need for expansion. So, not long after his arrival, he embarked on the mission to grow his team. Within the last year-and-a-half, he has welcomed six new faculty, and they’re already making a difference in the way the division serves its patients.

For Gupta, that was the objective—providing better patient care. It’s a large undertaking considering Children’s massive catchment area—the entire state of Alabama along with surrounding states. “Every disease state we have is in the hundreds,” he said. “And the doctors we had in those areas were just one or two.”

Intestinal rehabilitation, or ‘short gut,’ is a good example. It’s a complex issue affecting more than 160 of the team’s patients. But previously, only one doctor was available to serve them. With inflammatory bowel disease (IBD), the team had two doctors for more than 400 patients. The math was similar for patients with liver issues. “There was such a need to bring [new hires] in to just serve what we have,” Gupta said. “We were simply to trying keep our heads above water.”

To address these issues, Gupta began the process of expanding the division in September 2024, making all of the new hires over the course of the next year. In the case of IBD, the expansion was transformative. That group now has two new clinicians, Rahmath Althaf, D.O., and Maggie Vickers, M.D., and a basic scientist, Babajide Ojo, Ph.D. “Now, what we have is basically a team that goes from bench to bedside,” Gupta said. “We are starting studies where we are collecting samples from patients in the clinic, and then [Ojo] is processing these in the lab to do the studies. And with the discoveries he will make, we can then bring the knowledge back to the bedside.”

It’s an “ecosystem” that Gupta believes has not existed in gastroenterology at Children’s. The team has study coordinators and is part of national consortia. “So basically, we are creating a self-dependent and interdependent team of itself that can grow on its own,” he said.

Gupta aspires to create the same setup for intestinal rehabilitation. In the meantime, care is already improving. With Sirine Belaid, M.D., joining the team, the division now has two doctors to treat these patients, allowing them to see inpatients twice each week instead of once. “So now we are able to better serve the people more intentionally, more mindfully,” Gupta said.

Gupta also added liver doctors in David Willcutts, M.D., and Stephanie Saaybi, M.D., who “will helps us grow the liver team further,” he said.

Perhaps the most salient sign of the team’s success so far is this: patients who once had no choice but to go hundreds of miles away for treatment are now able to stay in Alabama for their care. “They are now being sent back to us by the doctors, who are saying, ‘Hey, UAB has a great program—go back there, you don’t need to come see us anymore,’” Gupta said. “So that has been very fulfilling that people are recognizing we are ace-ing our game here.”

With changes of this magnitude, Gupta believes the division can start to move from excellence to eminence, which was another of his goals when he first arrived.

New hires since September 2024

Rahmath Althaf, D.O., an assistant professor, earned her medical degree from the Touro College of Osteopathic Medicine. She completed her residency in general pediatrics at the Medical College of Georgia and her pediatric gastroenterology fellowship at UAB. Her research and clinical interests include IBD and intestinal ultrasound.

Sirine Belaid, M.D., an assistant professor, earned her medical degree from the University of Pittsburgh. She completed her residency in general pediatrics at the University of Iowa Stead Family’s Children’s Hospital and her pediatric gastroenterology fellowship at the University of Pittsburgh Medical Center.

Babajide Ojo, Ph.D., an assistant professor, earned his doctoral degree in nutritional sciences from Oklahoma State University. He completed his postdoctoral research at Stanford University School of Medicine. He received the NIH MOSAIC K99/R00 award in 2023. His research interests include using patient-derived intestinal organoids and murine models to determine how the environment (dietary components, therapies) shapes epithelial metabolism and differentiation in intestinal health and inflammatory bowel diseases.

Stephanie Saaybi, M.D., an assistant professor, earned her medical degree from the American University of Beirut in Lebanon. She completed her residency in general pediatrics at MedStar Georgetown University and her pediatric gastroenterology fellowship at UAB. She completed an additional fellowship in pediatric advanced hepatology and liver transplant at Northwestern University.

Maggie Vickers, M.D., an assistant professor, earned her medical degree from UAB. She completed her residency in general pediatrics and her pediatric gastroenterology fellowship at the Le Bonheur Children’s Hospital, St Jude Children’s Research Hospital and Regional One Health. Her clinical interests include general gastroenterology, nutrition and inflammatory bowel disease.

David Willcutts, M.D., an assistant professor, earned his medical degree from the University of Texas Southwestern Medical Center, where he also completed his residency in pediatrics and his pediatric gastroenterology fellowship. He completed an additional fellowship in pediatric advanced hepatology and liver transplant at the University of Colorado.
Neonatology

How Children’s Neonatologists Are Playing a Crucial Role in Complex Surgeries

Children’s neonatologists work with surgeons on many types of complex cases. (File photo)

In the Level IV Neonatal Intensive Care Unit (NICU), Children’s of Alabama cares for some of the sickest neonates in Alabama and the surrounding region. The unit, which expanded in 2025, frequently receives referrals from other hospitals for surgical and subspecialty care. Often, the babies cared for on the unit have conditions that require complex surgeries. In these cases, neonatologists work with surgeons and other specialists to manage the patient’s care. Jaw distraction is one example of a procedure they may manage.

Jaw Distraction Surgery and the Role of Neonatology

For some infants, a small or recessed jaw creates serious problems with breathing and feeding. Jaw distraction surgery—also called mandibular distraction osteogenesis—is an option that may dramatically improve outcomes for these patients. While the surgery itself is performed by craniofacial surgeons, the care before and after is deeply collaborative. Neonatologists play a central role in guiding babies and families through every step of the process.

Physicians typically consider jaw distraction surgery for young infants, often within their first month or two of life. Babies with the condition often work harder to breathe normally. They also may have difficulty feeding by mouth because the small jaw narrows the airway. If growth alone doesn’t lead to improvement, then a multidisciplinary team, including neonatologists, craniofacial surgeons, and often ear, nose, and throat (ENT) surgeons, evaluates whether jaw distraction could improve their symptoms and quality of life.

Surgeons focus on the technical aspects of lengthening the jaw, but before and after the operating room, neonatologists manage the airway, ventilation, nutrition and pain control. After the procedure, the baby returns to the NICU sedated and temporarily paralyzed. This protects the infant’s airway and allows the surgical site to heal while the jaw is gradually lengthened over several days. During this time, infants require ventilator support, careful airway management, pain control and nutritional support.

“This isn’t a procedure we recommend lightly,” Children’s of Alabama neonatologist Hannah Hightower, M.D., explained. “Protecting the airway is our number one concern for infants who undergo this surgery.” Because surgeons place hardware in the jaw, any movement could risk complications. This also means post-op babies cannot be held. This period can be especially hard on new parents who may have already begun holding and feeding their child.

As recovery progresses, collaboration becomes increasingly important. Neonatologists and surgeons work together to determine when it is safe to reduce sedation, remove the breathing tube and transition the baby off respiratory support. “Then, we begin working on the infant’s oral skills, because our ultimate goal is for the family to be able to feed their baby at home,” Hightower said. Many of these infants require tube feeding at first, but most eventually learn to feed by mouth.

Even in ideal cases, infants typically remain hospitalized for several weeks as they recover, learn to eat and prepare for discharge. Parents play a significant role as the baby’s recovery progresses, becoming actively involved in feeding and comforting their child. Success after jaw distraction is measured in practical, meaningful ways, such as improved breathing without respiratory support and the ability to take feeds by bottle.

Though the procedure can seem daunting, Hightower emphasizes its impact. Jaw distraction surgery can transform the course of an infant’s life—turning a situation marked by breathing struggles and feeding challenges into one where a baby can go home, breathe comfortably and be fed by their family. “It’s remarkable how a child who is working to breathe and unable to eat may improve and gain these skills post-surgery,” Hightower said. “Being able to send a child home doing those normal baby things is a big deal for the parents.”

Hematology and Oncology

Finding Novel Treatments for Cancer

The Developmental Therapeutics team at Children’s of Alabama is working to develop new treatments for children with cancer.

Having cancer is challenging enough for a child and their family, but when the standard treatments aren’t working, they find themselves searching for answers. As Director of Developmental Therapeutics at Children’s of Alabama and the University of Alabama at Birmingham (UAB), Jamie Aye, M.D., is responsible for finding those answers.

Aye was appointed to the position in August 2025 after serving as associate director since 2023. In her current role, she leads a team dedicated to developing more effective, less toxic therapies for children with cancer. In some cases, the cancers are rare; in other cases, the cancers are recurrent with no available curative treatment. Either way, developmental therapeutics can offer the possibility of a solution.

“It provides the family with hope that we will discover newer options that their cancer hasn’t seen,” said Aye, who’s also an associate professor of Pediatrics at UAB.

The team achieves this through a two-pronged strategy. One prong involves working to develop new therapies for cases that are recurrent or difficult to treat. “It’s really hard to see a patient go through that,” Aye said. The other prong is developing less-toxic therapies that reduce immediate and long-term side effects—for example, “If we’re able to use a new immunotherapy in conjunction with radiation that allows us to give the radiation at a lower dose,” Aye said, “now that patient has a lower risk for a secondary cancer from radiation.”

The program has a history of success. A few years ago, Gregory Friedman, M.D., one of Aye’s predecessors, led a successful early phase trial that used a new type of immunotherapy to treat patients with recurrent or progressive brain tumors.  Friedman’s novel treatment was the result of an investigator-initiated trial, where the team takes the work its researchers are doing and turns it into a clinical trial. Developing these types of trials is the overarching goal of the program. And the research avenues are broad, Aye says, “from researchers within pharmacology, radiology, immunology or genetics,” to name a few. Aye works to bring these researchers together “so that hopefully we can see commonalities between the different projects that we’re working on, so that people aren’t siloed and can collaborate through either new technologies, new biomarkers to measure how much disease, new immunotherapies, or new ways of detecting disease by imaging,” she said.

Any type of research the team is doing has the potential to turn into an effective treatment. “It could even just be a pathway a researcher is investigating,” Aye said. “Hopefully through collaborations that we’re establishing, we can see how that pathway may relate to a particular cancer that we’re hoping to find a treatment for—and then from that, test a new therapy, and then if it works in the lab, seeing how we can get it to a patient.”

Collaborations are one of the keys to making these trials happen. As director of the program, Aye works to build relationships both near and far. Locally, she leads an annual research retreat to bring together researchers—both basic science and clinical researchers—to work on developing investigator-initiated trials using novel therapies. She developed this retreat during her time as associate director of the program. Nationally, she works with industry and pharmaceutical companies—to investigate new therapeutic options—and with consortia to add to the program’s portfolio of trials available to patients at Children’s and UAB.

Aye is already working toward more investigator initiated trials, “which, hopefully in the coming years, will come to fruition,” she said, to provide more options and more hope for children with cancer. “It’s why we do what we do,” she added. “Because we want to improve their outcomes and also find treatments that don’t leave them with lifelong side effects.”

Hematology and Oncology

King providing psychological help for patients with sickle cell

Kathryn King, Ph.D., leads a new program designed to help patients with sickle cell disease manage psychological challenges.

Pain is as much a part of sickle cell disease as white lights are a part of Christmas. It’s what lands kids in the emergency room and hospital; severely affects their quality of life; and leaves them constantly on guard lest it return.

Less visible—but just as real—are the emotional, cognitive, and psychological burdens that accumulate over years of living with the condition.

Now, Children’s of Alabama has a new program designed to address the non-physical aspects of the disease. Funded by a generous donor and developed by pediatric psychologist Kathryn “Kate” King, Ph.D., the program’s aim is to help kids with mental health issues related not only to their disease but to the stress of growing up in today’s world.  

“Our kids and teens with sickle cell experience a lot of different psychosocial issues,” King said. “But first and foremost, they’re kids and teens. There’s so much that comes up that’s not even related to their sickle cell. But then it ends up impacting their sickle cell.”

Like their peers, they experience anxiety, depressed mood, stress and the challenges of growing up. But layered on top is a disease marked by chronic pain, complex treatment regimens, frequent medical visits and, for some, cognitive effects related to the disease itself.

When Pain Becomes Chronic

Sickle cell pain is often thought of as acute flares that are treated and subside. But for many children and adolescents, King said, the pain becomes chronic. “It starts to become more frequent and the pain signaling becomes more like a faulty fire alarm,” she said, continuously going off even when there’s no smoke.

At that point, medication alone is often not enough.

So an important focus is boosting patients’ ability to cope with pain. That includes evidence-based strategies such as diaphragmatic breathing and guided imagery to calm the autonomic nervous system and reduce the intensity of pain signals.

And it works. Screening tools find patients’ pain scores dropping several points after using such strategies even before receiving pain medication, King said.

Equally important is helping kids and their families reframe the pain. Understanding when pain is severe enough to require escalation to the hospital and when it can be managed while continuing daily activities can reduce fear and help maintain normalcy.

Another focus is helping adolescents transition to self-management. This period during adolescence is known for high rates of treatment lapses and worsening outcomes as kids try to become more independent with this complex disease.

“They’re managing so many different treatments and medications” so adherence drops, King said. “It could be forgetfulness, because they can experience cognitive issues related to sickle cell, but sometimes it’s more about not wanting to feel different.”

King teaches her patients to use alarms and visual reminders to improve adherence, and she works with parents to help them understand when to hand over responsibility to their child. Some parents struggle to let go, she said, while others step back too quickly.

The goal is a gradual, scaffolded approach. “The parent can still function as the safety net, but the patient is progressively learning the needed skills to become their own safety net.”

King tries to see patients in conjunction with their medical appointments. She also follows them when they’re hospitalized and offers telehealth visits. With nearly 1,000 patients in Children’s sickle cell program and just one dedicated psychologist, however, demand far exceeds capacity. Currently, she sees about 20 patients a week, with plans to grow gradually.

“My goal is to extend to as many of those as I can,” she said. “But there’s just one of me.”

She’s also focused on tracking data for the program, including barriers and facilitators for care, as well as outcomes. She’d eventually like to publish on the program’s experience to help other hospitals start their own.

Behavioral Health

The Crucial Role of Group Therapy in the Mental Health Crisis

In the midst of the mental health crisis, group therapy is proving to be an effective and efficient option. (Stock photo)

To say that today’s behavioral health providers are overwhelmed might be an understatement. In a time when many adolescents are struggling, therapists’ help is in high demand. Seeing all patients in a timely manner can be challenging. But for some providers, including the Children’s of Alabama behavioral health team, group therapy is showing promising results as an effective—and efficient—way to help the vast number of patients who need their support.

Group therapy is nothing new—Children’s has been offering it for years. For adolescents in particular, it has great potential. “Pediatric patients really tend to respond well to the social aspect of a group,” said Debra Patterson, Ph.D., director of Psychology and Associated Services at Children’s. “We do know, especially among early teens and adolescents, one of the things that makes them tick is to compare themselves to peers, as opposed to parents.”

In group therapy, a young person can get this. Instead of sitting in a room with two parents and a therapist—as they would in individual therapy—they’re working with five to 10 of their peers and maybe only two adults. “So it creates, for a pediatric population, an environment that is perceived as being more comfortable and more relatable than individual therapy.”

Relatability is part of what makes group therapy effective. For many adolescents, Patterson says, therapy continues to carry a stigma. They might say, “I’m not going to go to therapy—that’s just for losers, or I’m not crazy,” she explained. But if they’re in a group, therapists can change their perception by pointing out that peers are also present. And when they see others who might be experiencing similar struggles, a light goes off. “That’s very validating to say, ‘Oh my gosh, that’s exactly what happened to me,’” Patterson explained.

For many participants, this experience and the resulting sense of belonging can be surprising. “What we hear consistently is, ‘I thought I would hate it, but now I love it—it’s the best thing that ever happened,’” Patterson said.

Parents can be equally impressed, she added, when they see their children using the skills they’ve learned in therapy.

Part of the reason for these surprise effects may be the misconception of group therapy. Parents, in many cases, view it as a sort of placeholder. For example, a parent might initially say they’d rather wait six to eight months for their daughter to see a ‘real therapist,’ when, in reality, it’s possible to “get just the same—if not better—results having her do this group in the next two months than what we can if you wait for a psychologist to see you in the next six or eight months,” Patterson said.

And the idea that individual therapy is that only way to see a ‘real therapist’ is also incorrect. Group therapy leaders “are the same professionals that you sit across from one-on-one—that are all just as highly trained—and the interventions are evidence-based,” Patterson said. It’s much different from a support group, which is often led by peers.

Group therapy also has the capability to produce the same results as individual therapy. “What the research is telling us is that group therapy is as effective and is equivalent to individual therapies for a really wide range of diagnoses,” Patterson said. These include anxiety, depression, bipolar disorder, thought disorders or schizophrenia, trauma-related disorders, personality disorders and others. Adolescents with problems related to social skills or self-control—which might show up in a patient with ADHD—are especially good candidates for group therapy.

But group therapy isn’t for everyone. “The one caveat is if someone has an anxiety, perhaps as a result of a very recent trauma, that is so severe that it’s almost paralyzing, that being in a group would cause them to withdraw,” Patterson said. In that scenario, the patient might need individual therapy first.

And sometimes, the type of group a certain patient needs may not be available. “We’re not just going to put them in the social skills group that doesn’t meet their need,” Patterson said. The patients must both be ready for group therapy and have access to the right group.

Age is also a factor in the decision. Patterson says her team focuses mostly on adolescents, but they can start with children as young as 8 years old in certain situations.

How Group Therapy Works

Each group includes five to 10 patients and one or two therapists. Each session is broken down into two parts, starting with a psychoeducational component, which can involve teaching for 15 to 30 minutes. The next step is having the patients apply the skills they’ve learned for anywhere from 45 minutes to one hour and 15 minutes.

The leader sets clear expectations. A patient must be willing to participate—with the understanding, of course, that they don’t have to share too much. “No one is ever expected to come in and spill their guts to all these strangers that you’ve never met before,” Patterson explained. Participants also must agree not to be disruptive. And they must respect the confidentiality of the other patients, understanding that they can’t share someone else’s personal information outside the group.

Each session starts with an explanation of these responsibilities. From there, a discussion can emerge, evolve and take on a life of its own. “What’s really interesting is when you begin to see the group dynamic emerge, so that they’re kind of doing the work with each other, so that the leader or the psychologist in the room is really more of a facilitator,” Patterson said. “And when you see that little piece of magic happen, that’s when you’re getting the extra benefit that the group can offer.”

But the benefits are not limited to the participants. For providers, group therapy can help them see their patients through a new lens. “It almost lets you be a fly on the wall, or gives you more insight into their day-to-day interactions,” Patterson said. “Because it’s one thing to hear from a child or teenager or their parent, ‘Oh, whenever anybody says this, this is what happens.’ But when you can see it in real time and you can see their body language, you can see their coping strategies that they’re using or not using. So it creates a little bit more of a real-life scenario in order to be able to evaluate and consider what’s going on with a kiddo.”

The group context also offers a level of efficiency that individual therapy can’t. For example, Children’s offers a focused pain coping group. By offering this in a group setting, a therapist can see help five patients at once instead of just one. “So in other words, we increase that provider’s ability to provide services by 500%, which is enormous, and these kids leave that group doing well and having all of the skills that they need, just as if they had sat one-on-one,” Patterson said.

Nationally, the scale of help that group therapy can provide is being recognized, as well. Research published by the American Psychologist in 2023 suggests that increasing group therapy by 10% nationally could increase treatment access for more than 3.5-million people.

“And so that just really demonstrates the amplification,” Patterson said.

Gastroenterology

A high-tech approach to improving IBD treatment

When Children’s of Alabama associate scientist Babajide Ojo, MS, Ph.D., was completing his doctoral degree at Oklahoma State University, one of his peers had a child with Crohn’s disease. Ojo was so struck by the burden of the condition and its treatment on the child and his classmate—who eventually had to drop out of the program—that he decided his research must focus on inflammatory bowel disease (IBD), which includes Crohn’s and ulcerative colitis.

“I realized there were ways to manage the disease but no cure, so I thought it could be a great opportunity to contribute to this field and find better ways to treat it,” said Ojo, who’s also an assistant professor of pediatrics in the Division of Gastroenterology, Hepatology, and Nutrition at the University of Alabama at Birmingham (UAB).

Five years later—and a year after he arrived at Children’s—Ojo has already made an impact, using a newer, high-tech method to tease apart why IBD starts and what makes it flare in hopes of optimizing ways to control it. While most IBD treatments concentrate on calming the immune system, they don’t often lead to long-term remission, especially in children. So Ojo and his colleagues are looking at a different piece of the puzzle: the epithelium, or lining of the gut, which is important in IBD but often overlooked in research.

“The field right now solely focuses on the immune component of the disease,” he said. “But the data indicates that a lot of patients lose response to medications over time. For us, I think focusing on the epithelium may help us discover a kind of treatment that can elongate remission in these patients.”

Ojo is using a cutting-edge approach called patient biopsy-derived organoids—tiny 3D models grown from patient tissue—to watch how gut stem cells grow and become different kinds of cells that comprise the gut lining. By doing this, he hopes to understand how this process differs in people with IBD.

“Among the models we have, organoids may be one of the perfect ones to study the epithelium,” Ojo said, noting that few other pediatric centers use human-derived organoids for research. “Because each one represents the molecular features of each patient, it may be a way of developing personalized treatments.”

Based on his organoid research, Ojo and his colleagues published findings in December 2025 in Nature Communications suggesting that blocking a key fat-control protein helped epithelium cells in children with ulcerative colitis to burn energy more normally, reduce stress and calm inflammation. The results indicate that fat metabolism problems in colon cells are a major contributor to ulcerative colitis, potentially pointing toward new treatment approaches.

By identifying epithelial-specific “control points” central to IBD, Ojo hopes therapies can be developed that, if they don’t work for all patients, could be used specifically in pediatric patients.

“This may supplement some of the immunotherapies on the market to help us help them achieve long-term remission,” he said. “If we don’t improve how we treat patients, IBD is really a lifelong disease. We hope to make it much more manageable and reduce their constant visits to clinic, if not eliminate them totally.”

Cardiology

Pulmonary Vein Stenosis: No Longer a Death Sentence

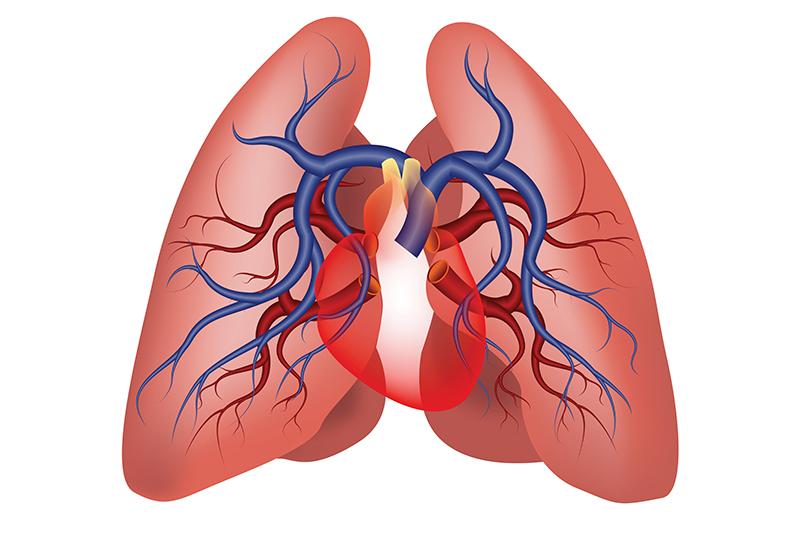
The pulmonary vein and artery system (Stock image)

Pulmonary vein stenosis (PVS) is a rare yet serious cardiovascular condition marked by progressive narrowing of the veins that return oxygenated blood from the lungs to the heart. Until recently, it was usually considered a death sentence. “There’s no two ways about it,” said Children’s of Alabama pediatric cardiologist Matt Clark, M.D. “It only gets worse once it starts.”

“When diagnosed, we would tell families there was nothing more to offer and to transition to end-of-life type care,” added pediatric interventional cardiologist Stephen Clark, M.D. “Until recently, we didn’t have medical therapies that could treat this. Surgical intervention was generally unsuccessful and sometimes accelerated the progression of the disease.”

Indeed, PVS has historically had grim outcomes, with mortality rates as high as 60% or more. Right ventricular pressure elevation—a marker of pulmonary hypertension (PH)—is strongly associated with mortality.

Now, there is hope.

“I think the biggest thing to come along was more data from studies and centers showing if you change the mindset and consider it as a possibly treatable condition, you change outcomes,” Matt Clark said.

That shift in mindset has driven a transformation in how PVS is diagnosed, monitored and treated. Today, children who would not have survived infancy are living into early childhood—and in some cases beyond—because of earlier recognition, aggressive catheter-based interventions and multidisciplinary care.

Earlier Detection, Closer Surveillance

One of the most important changes in PVS care has been earlier diagnosis, Matt Clark said, by recognizing high-risk populations: neonates with chronic lung disease; prolonged ventilation; those with congenital heart disease; and/or those with pulmonary hypertension (PH). The earlier the diagnosis, the more likely interventions are to be effective.

This surveillance-driven approach means clinicians are often identifying milder disease earlier—with regular echocardiograms, CT scans and diagnostic catheterization—and intervening at the first signs of progression.

PVS often exists in the setting of comorbid conditions such as PH, congenital heart disease or complications of prematurity, requiring close coordination between specialists. Thus, the pulmonary vein stenosis team in the Children’s of Alabama Heart Center has brought together a small group of pediatric cardiologists, allowing for shared memory and standardized decision-making.

“We don’t have to spend time reinventing the wheel,” Matt Clark said. “We can collectively remember all our patients” and which approaches approach worked best.

Catheter-Based Intervention as a Strategy, Not a Last Resort

Treatment for PVS has also evolved. Intervention includes balloon angioplasty to widen narrowed vessels or stent placement to hold them open. The stents are coated with sirolimus, a drug designed to prevent restenosis. However, rather than viewing catheter-based intervention to unblock the vessel as a one-time attempt to rescue a sick child, it is now viewed as a repeated, planned strategy.

“Every time you do an intervention,” Matt Clark said, “you’re signing that kid up for another cath at some interval.” That’s because the baby’s heart and lungs keep growing, requiring additional interventions. Multicenter analyses show that repeat catheterizations are associated with improved survival, reflecting a shift away from passive observation to active disease control.

In some children, repeated dilations and stent expansions over time allow pulmonary veins to reach near-adult size within the first few years of life.

Medical Therapy to Slow Disease Progression

Procedural care is now complemented by medical therapy aimed at the underlying biology of PVS.

Because the disease involves aggressive cellular proliferation within the vessel wall, antiproliferative medications such as sirolimus have become an important adjunct to intervention.

Observational studies suggest that children receiving systemic sirolimus have significantly improved survival compared with historical controls. In one widely cited cohort, four-year survival reached 100% in treated patients compared with approximately 45% in those not receiving therapy.

Sirolimus has also been associated with slower in-stent restenosis and longer intervals between interventions. While randomized trials are still lacking, these findings have helped legitimize systemic therapy as part of standard care at experienced centers.

“We’re probably doing more sirolimus-type therapies now than we used to,” Matt Clark said.

Survival Looks Different Now

Even with advances, PVS remains unpredictable. Not every child can be saved. But survival is no longer measured only in weeks or months.

Matt Clark described children who once would have died in the hospital now going home, growing and returning for planned interventions.

“One of the earlier ones was pretty impactful,” he said, recalling a child who lived long enough to spend two Christmases at home. “That was enough to make us keep going and keep pushing.”

“We know we’re helping,” he said. “So we’re more likely to intervene, to follow closely and to keep trying.”

Cardiology

Building a Team Around Pulmonary Hypertension

The Children’s PH team (L to R): Ahmad Khalil, Frank Bennett Pearce, Jodie Kanaday, Kevin Wall and Matthew Clark.

Pulmonary hypertension (PH) is a heterogenous condition stemming from numerous underlying causes, including extreme prematurity, congenital heart disease and systemic diseases like lupus. It causes dangerous increases in blood pressure in the lungs, straining the heart’s pumping ability and potentially leading to heart failure.

Care for children with PH has typically existed across silos: cardiology, pulmonology, neonatology and intensive care, said Frank Bennett Pearce, M.D., a pediatric cardiologist at Children’s of Alabama. Each discipline did its part. But clinicians increasingly recognized that the complexity of the condition and the fragility of the patients required greater coordination.

Today, a formal PH team of Pearce, pediatric cardiac critical care specialists Ahmad Khalil, M.D., and Matthew Clark, M.D., and pediatric cardiology fellow Kevin Wall, M.D., together with pediatric cardiology nurse specialist Jodie Kanaday, RN, round weekly on patients with PH to determine the best course of action for this rare but complex condition.

“We wanted to improve communication by having us all together saying the same thing to the consultant teams and to the families,” Pearce said.

That consistency matters, especially when care unfolds over weeks or months.

From a cardiology standpoint, PH has always been part of the landscape, Pearce said. “A lot of the treatment and diagnostic procedures like catheterizations and echocardiograms come through cardiology anyway,” he said. “So we end up being the treating doctors in lots of cases, or at least consultants.”

At the same time, many of the sickest patients are in neonatal and pediatric intensive care units and managed by critical care specialists.

PH is typically treated with medications like pulmonary vasodilators regardless of cause, but timing and diagnosis matter. That’s why it’s so important to have a precise anatomic diagnosis before starting medication, Pearce said. In babies with bronchopulmonary dysplasia, for instance, PH may be driven by acquired pulmonary vein stenosis—a condition that requires catheter-based or surgical intervention before medication.

Previously, decisions like these might have been made in parallel by different services. Now, they are made together.  

The team manages about a dozen inpatient pulmonary hypertension cases each month on inpatients at Children’s and the University of Alabama Birmingham (UAB). But inpatient care is only part of the story.

PH does not end at discharge. Medication management, insurance approvals, symptom monitoring and urgent questions follow families home. That’s where Kanaday, who is the Pulmonary Hypertension Clinic care coordinator, shines.

“We literally couldn’t do it without her,” Pearce said. She allows the team to see more patients, stay more organized and keep up with the paperwork/regulatory side of things in the PH world, he said.

Kanaday sees herself as a conduit to the physician. “Our patients know they can contact me directly for questions about medications, symptoms or side effects. I’m able to pass those concerns along quickly, which usually means they get help faster than they otherwise would.”

Her role, she said, is “making sure the doctors have all the information that they need to best take care of the patients.”

While the team is not formally tracking outcomes yet, Pearce says he’s seen a difference. “The patients are staying on their medications more consistently. The doses are more consistent. Some of these medications require a lot of paperwork—that’s getting handled quicker.”

In addition, the improved coordination means patients get to the cath lab sooner for pulmonary vein interventions. The team is also closely tied to newer catheter-based procedures, such as closing a patent ductus arteriosus or atrial septal defects in extremely small infants.

“I think it’s really been an asset to our cardiology team in general, taking this burden off of the general cardiologists and putting these patients with a provider who readily understands the disease process, available treatment options and possible complications. I think it makes our consult service much more efficient,” Kanaday said. “It has really made an impact on the patients, their continuity of care as an inpatient, and their follow-up in the outpatient clinic. I feel like we’re really making a difference and giving these kids the best chance to have positive outcomes long term.”

Urology

In New Role, Hopson Working to Address Sexuality in Patients With Spina Bifida

Betsy Hopson, Ph.D., MSHA, recently moved into a new role within the Division of Pediatric Urology.

Betsy Hopson, Ph.D., MSHA, describes her philosophy in one word: listen.

“Early in my career, I adopted this principle that if I heard the same story from two or more patients then it was either a research question or a quality improvement opportunity,” she said.

That mindset has shaped nearly two decades of work at Children’s of Alabama and the University of Alabama at Birmingham (UAB) and now underpins her new role as an assistant professor and health scientist in the Division of Pediatric Urology. There, she will direct a clinic dedicated to helping children with congenital urologic conditions transition to the adult health care setting.

Hopson began her career at Children’s in 2006 as coordinator of the Spina Bifida Program in the Division of Pediatric Neurosurgery. Yet she spent nearly as much time interacting with urology, she said, which plays a central role in bladder management for patients with the disease.

Her early work focused on helping patients make the difficult transition from pediatric to adult care. After realizing that young adults with spina bifida were aging out of pediatric clinics without clear adult pathways, she returned to school to earn a master’s degree in health care administration and then built an internationally recognized transition model.

It was listening to her patients, however, that led to the next chapter in her life.

In one case, a 15-year-old adolescent asked her about her research. When she told him it was sexual and reproductive health, “He whispered, ‘Betsy, I can’t do that, can I?”’

“Can’t do what, buddy?” she asked. “Date or have sex,” he answered. “That’s not for me, is it?”

Or the newly engaged, college-educated young woman with spina bifida who burst into tears when Hopson started discussing birth control with her. “You mean I can get pregnant?” she said. “I had no idea.”

“If this young woman who is very educated had no idea,” Hopson said, “what is this like for the rest of the population?”

And a light bulb went off. “We’re telling them we want them to be independent, that we want them to take care of themselves, but we’re not giving them any carrot or showing them what’s possible and helping them paint that picture of what adult life could look like.”

Her “eureka” moment led her back to school to obtain her Ph.D. in Rehabilitation Science and a certificate in Mixed Methods Research. Her goal was to understand gaps in sexual health education for people with congenital diseases like spina bifida. What she uncovered was far more troubling.

“Because these patients are prescribed catheterization for bladder management early in life,” she said, “they’re taught the technical skills of catheterization but not taught about personal boundaries and appropriate touches.”

Her research found that 46% of adults with spina bifida reported a history of sexual abuse. For her dissertation, she validated a clinical screening tool to identify abuse risk and gaps in sexual health knowledge.

In her new role with the urology team, she sees her goal as twofold: “One is to help support normal development,” she said. “I want to normalize sexual and reproductive health conversations so patients can see what’s possible and give them space to imagine a full adult life.”

The other involves educating patients, parents and clinicians about the increased risks vulnerable patients face and developing tools for clinicians and families to identify and talk openly about those risks.

It’s important, she noted, to bring the parents into the discussion. “When you bring [sexuality] up in the clinical setting in front of their child, they might be initially hesitant.” Her solution is the same approach that has guided her career: listen first. That means holding focus groups with patients and parents to shape new curricula and ensure the content reflects lived experience rather than clinician assumptions.

“If there’s one thing my career has taught me,” she said, “it’s to never stop learning and never stop looking for ways to make a difference.”

Cardiology, Inside Pediatrics

Lau shares vision as new Physician-in-Chief

Yung Lau, M.D. was named physician-in-chief at Children’s of Alabama and chair of the UAB Dept. of Pediatrics in March 2025.

After serving as interim chair for five months, Yung Lau, M.D., was officially named chair of the University of Alabama at Birmingham (UAB) Department of Pediatrics and physician-in-chief at Children’s of Alabama in March 2025. The only real change, Lau said, was that he could now formally begin planning for the future. His vision for the department is expansive—centered on collaboration and faculty support. But he believes the path to those big goals lies in the small things everyone does every day.

Lau stepped into the interim chair role in November 2024, following the announcement that then-chair Mitch Cohen, M.D., would be departing at year’s end to join Stanford. “Dr. Cohen led for a decade and helped build this department into a strong and vibrant group,” Lau said. “It has consistently thrived, and I’ve considered it a privilege to be a part of the department as a faculty member for over three decades. Now, it’s an awesome responsibility to carry on this tradition of excellence.”

The role requires close collaboration between two major institutions: Children’s of Alabama and the University of Alabama at Birmingham. With more than 30 years of experience across both organizations—including in leadership roles—Lau understands their individual missions and how they intersect.

That understanding came into sharp focus in 2007, when Lau led the UAB group in a major collaborative effort between the two institutions. At the time, UAB housed the pediatric cardiac program. But as Children’s leaders planned to build a new hospital tower, they wanted to bring the program under their roof. Over the next five years, Lau played a significant role in bringing physicians and other clinical staff to assist in the design of the cardiac intensive care units, operating rooms, catheterization labs, step-down units and cardiovascular perioperative areas. He then worked closely with Children’s leadership on staffing and operations planning. On October 14, 2012, the program moved into the new building—seamlessly.

The success of the move laid the foundation for a quantum leap in the ability of the Pediatric and Congenital Heart Center of Alabama to provide state-of-the-art care. Today, the program consistently ranks among the top performing pediatric and congenital heart centers in the nation by numerous metrics, and the Society of Thoracic Surgery has classified the program as an overperforming center—one of 12 in the country. For Lau, who served as the division director of pediatric cardiology from 2012 until his appointment as chair in 2025, the experience left a lasting impression about what’s possible when Children’s and UAB work together.

“The opening of the Heart Center marked one of the most satisfying periods of my career,” he said. As he steps into his new role, he hopes to lead more collaborative efforts with similarly meaningful impact.

The Heart Center’s success is a powerful example of the synergy between Children’s and UAB—a synergy Lau believes can grow even stronger. “What I’ve seen is a real willingness among leadership across both institutions to reduce barriers and connect silos,” he said.

Lau has outlined three key priorities to strengthen that collaboration: maximizing current resources in clinical care, education and research; strategically recruiting and developing faculty; and building a resilient foundation of financial stability and physician well-being.

Education and research are crucial parts of his strategy, and UAB and Children’s have a history of successful collaboration on both. From an education perspective, Children’s serves as the teaching hospital for the UAB pediatric medicine, surgery, psychiatry, research and residency programs. “There’s this deep core of understanding between Children’s and the department that we are really training the future physicians for the state,” Lau said. And that’s a crucial role in a state that, Lau says, needs more physicians and pediatricians. “Part of our duty here is in our obligation to do that,” he added.

On the research side, the two institutions work together to “advance knowledge for the children of Alabama and beyond for the future,” Lau said. This benefits both entities, sometimes leads to advancements and breakthroughs that influence the broader world of medicine, and enhances the reputation of both.

“When we collaborate more extensively and continue to strengthen those ties of collaboration, two important things happen,” he said. “First, children receive better care, now and in the future. Second, our faculty experience significantly greater job satisfaction.”

Faculty support is another central pillar of Lau’s vision. Since becoming chair, he has met with many faculty members—some he’s long known, others he’s come to know better through these conversations. What stands out most, he says, is their passion and the profound impact they have on children’s lives. His goal is to listen, support and help them succeed.

Lau also acknowledges the tension between moral obligation and financial reality. “That’s just medicine in America today,” he said. But he’s confident the department can thrive within that framework.

“I think both institutions understand that we need to maximize our resources—our people and infrastructure—to provide the best possible care, to train the next generation of pediatricians, and to innovate through research,” he said.

Though there are multiple facets to Lau’s vision, everything is focused around the patient.

“The patients in front of us are the cornerstone of everything we do,” he said. “And while our goals may be big, the real progress happens in the small steps we take every day.”

“Yes, having a goal is important,” he continued. “But sometimes if we focus only on the goal, we risk losing sight of what’s happening in the moment—and that can distort the work being done on the ground. Sometimes the things that matter most get sidelined in the name of progress.”

With a strong focus on the patient—and through strong collaboration and faculty support—Lau believes UAB and Children’s will continue to deliver exceptional care to every child they serve.